Retatrutide and birth control — 6 critical facts to know.
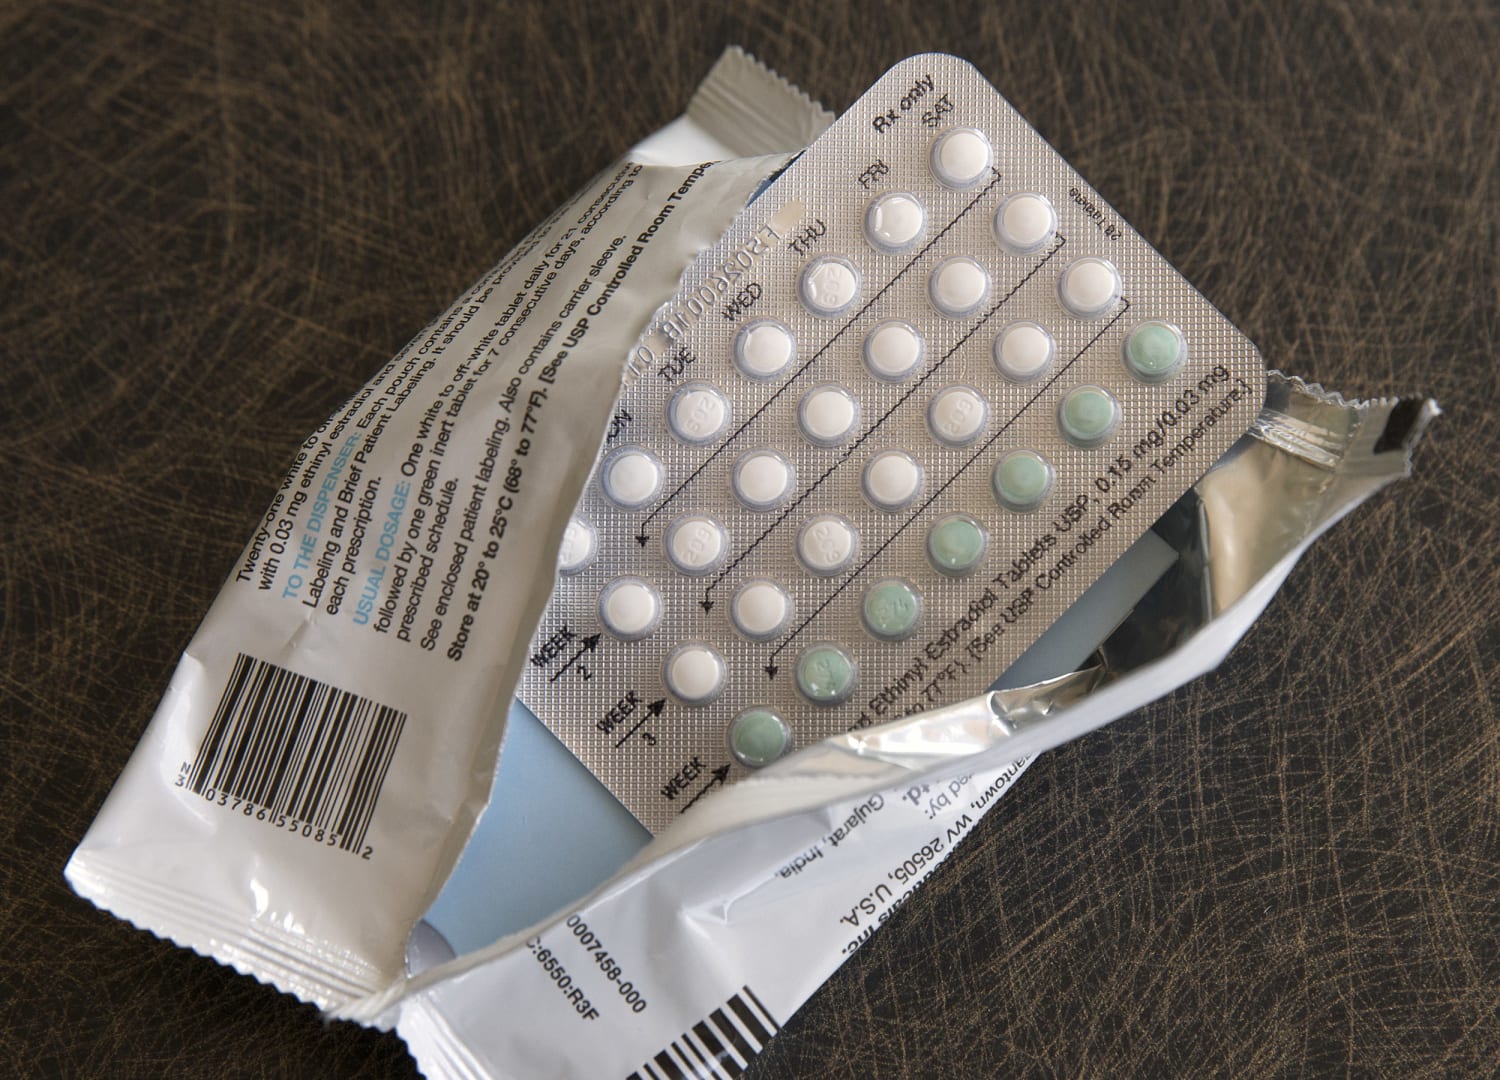
Retatrutide and birth control is a question that deserves a genuinely careful answer, because getting it wrong has real consequences. While retatrutide itself has no dedicated interaction studies yet — it remains unapproved — mechanistically similar medications already on the market have documented, clinically meaningful effects on oral contraceptive absorption.
This guide explains the mechanism behind this interaction, what has actually been studied in similar medications, why retatrutide’s specific mechanism makes this relevant, and what to discuss with a healthcare provider. This is educational content — retatrutide is not an approved medicine, and nothing here constitutes medical advice. General contraception guidance is available through the NHS.
See our full range of GLP-1 treatments with 24/7 expert support.
Explore Mounjaro →Retatrutide and birth control — fact 1: the underlying mechanism
GLP-1 class medications work partly by delaying gastric emptying — slowing how quickly food and, importantly, oral medications move from the stomach into the small intestine, where most absorption actually happens. This delay is central to how these medications reduce appetite, but it has a secondary effect worth understanding.
Oral contraceptive pills need to be absorbed reasonably quickly and consistently to maintain the steady hormone levels that prevent ovulation. If gastric emptying slows significantly, the timing and completeness of that absorption can shift, which is the mechanism behind the retatrutide and birth control concern.
Retatrutide and birth control — fact 2: what Mounjaro’s data shows
The clearest evidence in this entire area comes from tirzepatide (Mounjaro), not retatrutide directly. A clinical study evaluating this exact interaction found that a single 5mg dose of tirzepatide reduced overall oral contraceptive hormone exposure by approximately 20% — a clinically meaningful reduction.
As a direct result of this finding, Mounjaro’s manufacturer recommends that patients using oral contraceptives switch to a non-oral method, or add a barrier method such as condoms, for four weeks after starting treatment and after each subsequent dose increase. This recommendation reflects the fact that the effect on gastric emptying is believed to be strongest shortly after these transition points.
| Medication | Mechanism | Documented oral contraceptive effect |
|---|---|---|
| Tirzepatide (Mounjaro) | GIP + GLP-1 | ~20% reduced exposure — manufacturer recommends backup contraception |
| Semaglutide (Ozempic/Wegovy) | GLP-1 only | No clinically significant effect found |
| Liraglutide, dulaglutide | GLP-1 only | No clinically significant effect found |
| Retatrutide | GIP + GLP-1 + glucagon | No dedicated study published — mechanistic overlap with tirzepatide is notable |
Retatrutide and birth control — fact 3: not all GLP-1s are equal here
This is an important nuance often lost in general GLP-1 discussions. Semaglutide (Ozempic, Wegovy), liraglutide, and dulaglutide — all of which act on the GLP-1 receptor alone — have not shown the same clinically significant reduction in oral contraceptive absorption in available studies, despite also delaying gastric emptying to some degree.
The documented interaction appears specifically tied to tirzepatide’s dual GIP/GLP-1 mechanism, suggesting the additional GIP receptor activity may play a specific role in the magnitude of the gastric emptying effect relevant to oral drug absorption, rather than gastric slowing from GLP-1 activity alone being sufficient to cause a clinically meaningful reduction.
Retatrutide and birth control — fact 4: why retatrutide is relevant here
This is the crux of the retatrutide and birth control question. Retatrutide shares tirzepatide’s GIP receptor activity, and adds glucagon receptor activity on top — making it mechanistically at least as likely, and plausibly more likely, to produce a similar or greater effect on gastric emptying and oral drug absorption.
To be clear, no dedicated clinical study of retatrutide’s effect on oral contraceptive absorption has been published, since retatrutide has not gone through the same regulatory interaction-study process as an approved medicine. This is an area of reasonable mechanistic concern based on tirzepatide’s data, not a confirmed, measured finding specific to retatrutide.
Everything about retatrutide and birth control interaction risk in this article is reasoned from tirzepatide’s documented data and shared mechanism, not from a retatrutide-specific study. Treat this as a plausible, mechanistically grounded concern worth discussing with a doctor — not a confirmed clinical fact with a known percentage.
Retatrutide and birth control — fact 5: the fertility consideration
There is an additional layer to the retatrutide and birth control conversation that is easy to overlook: significant weight loss itself can improve fertility, particularly in people who previously had irregular ovulation linked to excess weight or conditions like PCOS.
This means a missed or partially absorbed birth control pill during significant weight loss treatment may carry a higher chance of resulting in pregnancy than the same missed pill would for someone not experiencing that fertility improvement. This compounds the practical importance of reliable contraception during treatment with any GLP-1 class medication, retatrutide included once approved.
It is worth noting that this fertility effect is not unique to retatrutide or even to GIP-active medications specifically — any GLP-1 class medication that produces substantial weight loss carries this same consideration. Women who were not ovulating regularly before treatment, whether due to excess weight, PCOS, or other factors, may find their cycles becoming more regular as weight decreases, which is precisely the scenario where contraceptive reliability becomes most important.
Retatrutide and birth control — timing around dose changes
Understanding when the retatrutide and birth control interaction risk is likely highest helps translate the general precaution into a practical routine. Based on the tirzepatide data this guidance is extrapolated from, the effect on gastric emptying — and therefore oral drug absorption — appears most pronounced in the days and weeks immediately following a new dose, whether that is the starting dose or any subsequent increase.
This is consistent with how GLP-1 class medications generally behave — the body adapts somewhat to a stable dose over several weeks, with gastrointestinal effects including gastric emptying delay often becoming less pronounced at a steady, unchanged dose than immediately after a change. This is precisely why the four-week backup contraception window recommended for tirzepatide is tied specifically to dose transitions, not applied as a blanket recommendation for the entire duration of treatment.
- Starting dose: The first four weeks after any first dose warrant a backup contraceptive method, mirroring tirzepatide’s manufacturer guidance.
- Each dose increase: The same four-week backup window applies after every subsequent titration step, since each increase can reintroduce a period of adjustment.
- Stable maintenance dose: Once several weeks have passed at an unchanged dose, the absorption effect is generally expected to be less pronounced, though this has not been separately confirmed for retatrutide.
Retatrutide and birth control — fact 6: what to actually do
- Discuss your contraceptive method openly with any prescriber before starting a GIP-active GLP-1 class medication, including an eventual approved form of retatrutide.
- Consider a backup barrier method during the first four weeks after starting treatment and after any dose increase, mirroring the precaution already recommended for tirzepatide.
- Ask about non-oral contraceptive options — such as an IUD, implant, or injection — which are not affected by gastric absorption changes at all.
- Take oral contraceptives as consistently as possible, since the interaction risk compounds with any missed or delayed doses.
- Flag any unusual bleeding patterns to your prescriber, since this can sometimes — though not always — signal reduced hormone absorption.
Retatrutide and birth control is a topic where caution costs nothing and complacency could cost a great deal. Until retatrutide has dedicated interaction data of its own, treating it with the same caution as tirzepatide is the responsible, evidence-informed approach.
Our clinical guidanceFor more on retatrutide’s current status, read our guide on retatrutide’s regulatory status. Explore our Mounjaro product page for an approved option available today, or read patient reviews.
This article is for informational and research purposes only and does not constitute medical advice. Retatrutide is not currently approved as a medicine and has no dedicated drug-interaction studies published. Information regarding oral contraceptive interaction is extrapolated from data on mechanistically similar approved medications, particularly tirzepatide, and should not be treated as confirmed for retatrutide specifically. Always consult a qualified healthcare provider regarding contraception and any GLP-1 class medication before making any decisions about your treatment or family planning.
Common questions — retatrutide and birth control
Explore approved options with expert guidance.
UK-based, MHRA-compliant supply with 24/7 expert support to help you navigate treatment decisions safely.
Explore Mounjaro →