Blood pressure medication with retatrutide — 7 critical facts.
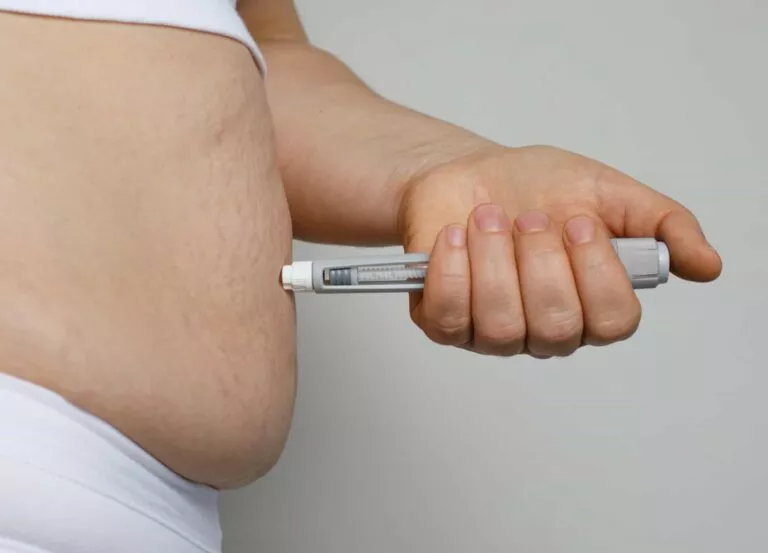
Blood pressure medication with retatrutide is one of the most practically important interaction questions for anyone considering this compound, since many people researching weight management are already taking antihypertensive medication. The short answer is reassuring — the combination is generally manageable — but the details matter more than with most drug interactions.
This guide explains how each major class of blood pressure medication with retatrutide interacts, why your existing BP dose may need reducing as treatment progresses, and the specific monitoring points that genuinely matter. For a broader overview, read our guide on retatrutide and high blood pressure. General cardiovascular information is available through the British Heart Foundation.
Transparent sourcing and quality documentation for your research.
Explore Retatrutide →Blood Pressure Medication With Retatrutide — fact 1: retatrutide lowers BP independently
The most important starting point for understanding blood pressure medication with retatrutide is that retatrutide itself produces meaningful blood pressure reduction. Phase 3 clinical trial data showed systolic blood pressure reductions of 8-12 mmHg at higher doses over 24 weeks — a clinically significant drop driven by both the weight loss itself and the compound’s direct metabolic effects.
This independent BP-lowering effect is the central reason why blood pressure medication with retatrutide requires closer attention than many other drug combinations. When you add a compound that lowers blood pressure by 8-12 mmHg on top of medication already prescribed to lower blood pressure, the combined effect can push BP lower than intended — sometimes significantly so.
Blood Pressure Medication With Retatrutide — fact 2: ACE inhibitors and ARBs
ACE inhibitors (ramipril, lisinopril, enalapril) and ARBs (losartan, valsartan, candesartan) are among the most commonly prescribed blood pressure medications — and they’re the class that requires the most attention alongside retatrutide. The additive blood pressure lowering from combining these with retatrutide can cause symptomatic hypotension, particularly orthostatic hypotension — dizziness or lightheadedness when standing up.
This additive effect is most pronounced during the dose escalation phase of retatrutide when the compound’s own BP-lowering effect is strengthening rapidly. Blood pressure medication with retatrutide in this combination requires monitoring at every dose escalation step, not just at the start of treatment, since each retatrutide dose increase adds another layer of BP reduction on top of the existing medication.
| BP medication class | Interaction concern | Monitoring level |
|---|---|---|
| ACE inhibitors / ARBs | Additive hypotension, orthostatic risk | Close — at every dose escalation |
| Beta-blockers | Additive hypotension + masks hypoglycaemia signs | Close — glucose monitoring essential |
| Calcium channel blockers | Additive hypotension (lower risk), absorption timing | Routine — standard BP checks |
| Diuretics | Dehydration compounding, electrolyte risk | Close — especially during nausea episodes |
Blood Pressure Medication With Retatrutide — fact 3: beta-blockers
Beta-blockers (atenolol, bisoprolol, metoprolol, propranolol) present two specific concerns when taken as blood pressure medication with retatrutide. The first is the same additive hypotension seen with ACE inhibitors — retatrutide’s independent BP reduction compounds with the beta-blocker’s effect, potentially dropping pressure below comfortable levels.
The second concern is more specific and clinically important: beta-blockers can mask the warning signs of hypoglycaemia. A racing heart, tremor, and palpitations are the body’s normal alarm signals for low blood sugar — and beta-blockers suppress exactly these responses. If retatrutide is also being used alongside insulin or sulfonylurea-type diabetes medications, this three-way combination makes hypoglycaemia both more likely and harder to detect, which is a genuinely important safety consideration.
If you take a beta-blocker and are also using insulin or sulfonylureas alongside retatrutide, regular blood glucose monitoring becomes essential rather than optional. The beta-blocker can prevent you from feeling the usual warning signs of low blood sugar, meaning the first symptom you notice could be confusion or dizziness rather than the earlier tremor or heart-racing that would normally alert you.
Blood Pressure Medication With Retatrutide — fact 4: calcium channel blockers
Calcium channel blockers (amlodipine, nifedipine, diltiazem, verapamil) are generally the lowest-risk blood pressure medication with retatrutide combination in terms of interaction concerns. The additive blood pressure effect still applies, but is typically less pronounced than with ACE inhibitors or beta-blockers.
There is one pharmacokinetic consideration worth noting: retatrutide delays gastric emptying, which may slightly alter the absorption profile of extended-release calcium channel blocker formulations. This is a theoretical concern rather than one backed by specific clinical data with retatrutide, but for anyone on extended-release amlodipine or similar formulations, routine blood pressure monitoring is sufficient to catch any meaningful change.
Blood Pressure Medication With Retatrutide — fact 5: diuretics
Diuretics (hydrochlorothiazide, furosemide, indapamide, spironolactone) as blood pressure medication with retatrutide require specific attention because of the compounding dehydration risk. Retatrutide commonly causes nausea, reduced fluid intake, and occasionally vomiting or diarrhoea — all of which can lead to dehydration. Diuretics independently increase fluid loss through increased urination.
When these effects overlap, particularly during the dose escalation phase when gastrointestinal side effects are most pronounced, the combined fluid loss can become clinically significant — affecting kidney function, electrolyte balance, and blood pressure stability. Staying well-hydrated becomes an active priority rather than a passive suggestion, and electrolyte monitoring may be warranted during periods of pronounced nausea or reduced intake.
Blood Pressure Medication With Retatrutide — fact 6: your dose will likely need adjusting
This is perhaps the most practically important blood pressure medication with retatrutide fact: as treatment progresses and weight loss accumulates, many patients find their pre-existing antihypertensive medication becomes too strong at its original dose. What was the right dose before significant weight loss is often too much afterward, because the underlying reason for the elevated blood pressure — excess weight, visceral fat, arterial stiffness — has been meaningfully reduced.
Some clinical guidance suggests that downward adjustment of antihypertensive doses may be appropriate after several weeks on retatrutide as the metabolic improvements and weight loss reduce the cardiovascular load the original dose was prescribed to manage. This is genuinely a positive development — needing less blood pressure medication is a sign that treatment is working at a cardiovascular level, not just a cosmetic one.
The timing of this adjustment varies by individual, but it’s most commonly needed between months 2 and 6 of treatment — the period when cumulative weight loss is most substantial and the full blood pressure medication with retatrutide additive effect is most pronounced. Proactively discussing this possibility with your prescriber before it becomes symptomatic is considerably better than waiting until dizziness or lightheadedness forces a reactive dose change.
Blood Pressure Medication With Retatrutide — fact 7: what to monitor
Practical monitoring for blood pressure medication with retatrutide should include regular home blood pressure readings — ideally daily during the first month and at each dose escalation, then weekly once stable. A consistent pattern of readings below your target range, particularly with symptoms of lightheadedness, is the signal to discuss a dose reduction with your prescriber.
- Dizziness on standing — the most common sign of excessive additive BP lowering, particularly in the first 48 hours after a retatrutide dose.
- Persistent lightheadedness or fatigue — may indicate sustained over-lowering rather than a transient effect.
- Significantly reduced urine output or very dark urine — potential signs of dehydration compounding with diuretic use.
- Unexplained confusion or cognitive fog — can indicate either hypotension or hypoglycaemia, both of which are more likely during the blood pressure medication with retatrutide combination.
Blood pressure medication with retatrutide is manageable, not dangerous — but it requires active monitoring rather than passive coexistence. The reward for staying attentive is that many patients eventually need less blood pressure medication, which is one of the most meaningful health outcomes of the entire treatment.
Our research guidanceFor the full picture on cardiovascular effects, read our guide on retatrutide and high blood pressure. Explore our Synedica Retatrutide product page, or read patient reviews.
Retatrutide is not approved as a medicine anywhere. This article is for research and informational purposes only. Blood pressure interaction data is drawn from clinical trial reports and established pharmacological principles for the GLP-1 class. Never adjust blood pressure medication doses without consulting your prescriber directly.
Common questions — blood pressure medication with retatrutide
Explore verified retatrutide sourcing.
Transparent sourcing, quality documentation and 24/7 support for your research journey.
Explore Retatrutide →